 DrugClass
Explanation: Why Beta-Blockers Can Be Unsafe in Asthma
Understand beta-2 blockade, asthma risk, and why beta-1 selectivity needs careful interpretation.
Introduction: Why This Contraindication Matters
A patient has asthma and a heart condition. Can a beta-blocker be used? This question tests more than a drug name. It tests receptor selectivity and safe decision-making.
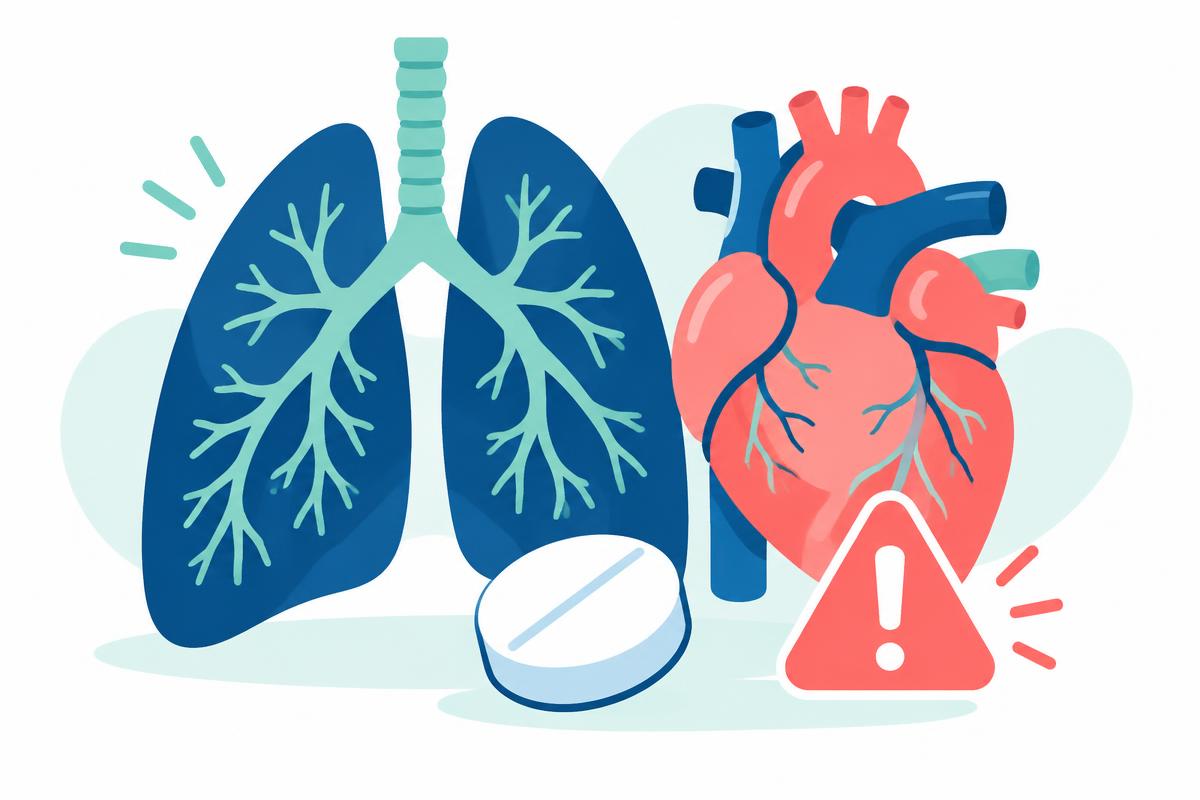
The simple exam link is non-selective beta-blocker → beta-2 blockade → bronchospasm risk.
But the statement “all beta-blockers are always forbidden in asthma” is too broad. A beta-1-selective medicine may be considered for a strong cardiac reason under careful medical supervision.
Easy-Learn: Classify Before You Decide
Separate Non-Selective and Beta-1-Selective Drugs
| Group | Examples | Asthma concern |
|---|---|---|
| Non-selective beta-blockers | Propranolol, Nadolol, Timolol | Block beta-2 receptors and can narrow airways |
| Relatively beta-1-selective blockers | Metoprolol, Bisoprolol, Atenolol | Lower beta-2 effect at usual doses, but risk is not zero |
| Alpha-1 plus non-selective beta blockers | Carvedilol, Labetalol | Additional alpha blockade does not remove beta-2 risk |
“Cardioselective” means relatively selective for beta-1 receptors. It does not mean a medicine acts only on the heart.
Remember the Eye-Drop Trap
Timolol eye drops can enter the bloodstream. They can still cause systemic beta-blockade and breathing problems. A medicine does not become risk-free because it is used in the eye.
Mechanism of Action: The Airway Door Analogy
Imagine airway muscles as a door that can become tight. Beta-2 stimulation helps loosen that door.
Salbutamol, a beta-2 agonist, sends an “open” signal. It helps the airway muscle relax.
Propranolol blocks the receiver for that signal. Airway muscles may tighten. It may also reduce the response to a beta-2 reliever medicine.
Why Beta-1 Selectivity Helps but Does Not Guarantee Safety
Beta-1 receptors are important in the heart. Blocking them can slow heart rate and reduce the heart's workload.
At lower doses, Bisoprolol and similar medicines affect beta-1 more than beta-2 receptors. As exposure increases, selectivity can decrease. Individual responses also differ.
Think of a selective blocker as a guard who usually watches one doorway. At higher exposure, the guard may start blocking another doorway too.
What can be asked in GPAT?
- Which receptor explains beta-blocker-induced bronchospasm? Beta-2.
- Why is Propranolol a poor choice in asthma? It is non-selective and blocks airway beta-2 receptors.
- Is Metoprolol absolutely beta-1-specific? No. Its selectivity is relative and dose-dependent.
- Can Timolol eye drops affect breathing? Yes. Systemic absorption can occur.
- Why might Salbutamol work less well after a non-selective beta-blocker? The blocker opposes beta-2 receptor activation.
These questions are for practice, not claims about a past or future GPAT paper.
Clinical Nuance and Quick Revision
For an exam stem, identify the named medicine first. “Beta-blocker” alone is not enough. Then check whether the question asks about non-selective blockade or supervised use of a beta-1-selective agent.
Evidence supports carefully selected use of cardioselective medicines in some patients with asthma when cardiovascular benefits are important. That is a clinician's decision, not a reason to self-start treatment.
A person already taking a beta-blocker should not stop it suddenly without advice. New wheezing or breathing difficulty needs prompt assessment.
Read the beta-blocker pharmacology review and the review of cardioselective beta-1 blockers in asthma.
For more simplified pharmacy notes and 50+ mock tests, visit our Pro Dashboard.
Take Free Test on this Topic
Check what you learned with quick GPAT-style questions.
Start Free Test →Unlock all 14 Classifications and 50+ Mock Tests with our Student Pro plan.
Unlock NowFor educational use only — not medical advice. Always check doses with current prescribing information.